mmonfar

I look at a hospital three ways.

Hospital executives face problems that no single view can resolve. I blend three: clinical, operations and people.

Martin Monteagudo FarinaMPH, PGCert Business Analytics, BSN, CPHQ

See the three views at workGet in touch

My reading map: the topics I read and link, flowing into one point.
My reading map: topics I read and link.

Who I am

Maths caught me as a child. It never let go.

That cross-domain vision is rare, and it is what I bring to the people who run hospitals. In my own time, I build it in the open.

Where I worked
  1. Mar 2025 to presentClinical Risk ManagerDubai Health (Al Jalila Children's & Latifa Hospital), DubaiUAE
  2. Jul 2021 to Dec 2024Quality and Patient Safety SpecialistAmana Healthcare (M42), Abu DhabiUAE
  3. Aug 2016 to Jul 2021Charge Nurse, Unit Council Chairman, Quality Committee MemberKing Faisal Specialist Hospital and Research Centre, JeddahSaudi Arabia
  4. Jul 2015 to Jul 2016Intensive Care NurseHospital Álvaro Cunqueiro (SERGAS), VigoSpain
  5. Aug 2012 to Jul 2015Renal, Cardiac Cath Lab and Recovery NurseManchester Royal Infirmary (NHS)UK
  6. Jul 2009 to Jul 2012Intensive Care NurseComplexo Hospitalario Universitario de Ourense (SERGAS)Spain

How I work

One hospital.
Three views. Blended.

An executive's problem rarely sits in one view. Each view asks one question. The answer needs all three together.

In development

A hospital you can open like a model.

From the campus down to one bed.

A hospital campus in 3D: main hospital, heart centre and outpatients. Picture of a model in development.

Open the 3D model (opens in new tab)

Synthetic data. Illustration only. Not a medical device.

Education, certification and papers

About

Who I am.

Tap a tab for my story or my credentials.

Portrait of Martin Monteagudo Farina

Maths caught me as a child. It never let go.

I started in civil engineering. Then I spent years in intensive care.

While I lived in the UK, I studied social anthropology at a distance. Half a degree, flying home to sit the exams.

Seventeen years across the UK, Spain, Saudi Arabia and the UAE. Four health systems. Different rules, the same pressure on beds.

So I look at a hospital three ways. Clinical: the patient in the bed, and how fast they can get worse. Operations: queues, beds, the bad weeks an average hides. And as people: the culture that decides what gets reported, and what does not.

That cross-domain vision is rare, and it is what I bring to the people who run hospitals. In my own time, I build it in the open.

Always up for a good conversation!

Credentials

MPH. PGCert Business Analytics. BSN. CPHQ. Two papers, two talks.

See the details

Education

Publications

Talks and teaching

Where I worked

Where I worked

The same problems, everywhere I worked.

Four health systems. Different rules, the same pressure on beds.

Instead of another meeting, I bring the evidence, the people's view and a tested plan.

Tap a place to see the hospitals. Published examples. Open a dot to see its source. See References.
Portfolio: the work

Portfolio

Nine projects. Three views.

Tap a video for a short preview. Code is on GitHub.

Clinical
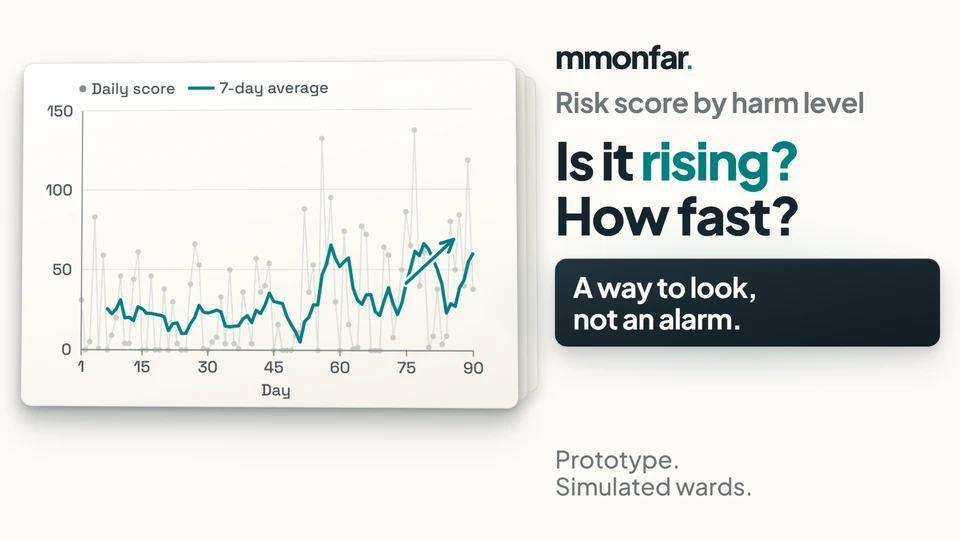
Is reported harm rising?

Operations

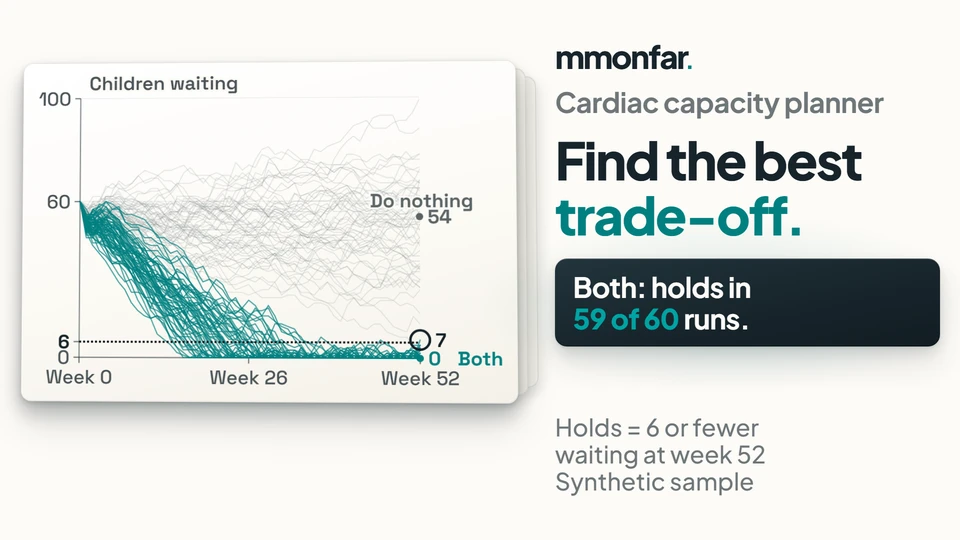
Does the plan still work in a bad year?

People

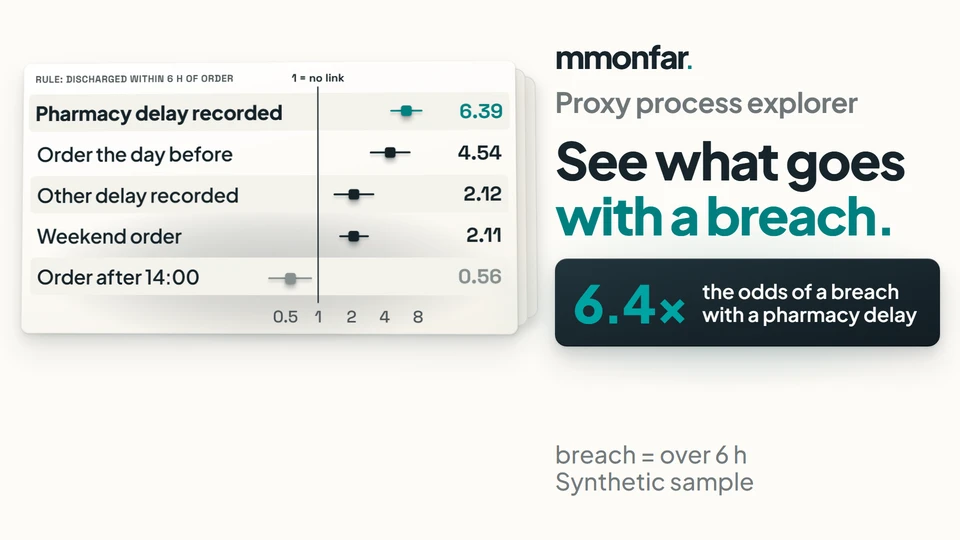
What really happens, step by step?

Contact

Let's talk.

Questions, ideas, a project you want to try, or a licence request: write to me.
Video

Example data. Not a real hospital.

Code on GitHub (opens in new tab)

References

Numbers match the notes on the problem cards.

  1. McCabe R, Schmit N, Christen P, et al. Adapting hospital capacity to meet changing demands during the COVID-19 pandemic. BMC Medicine. 2020. doi:10.1186/s12916-020-01781-w (opens in new tab)
  2. Grasselli G, Pesenti A, Cecconi M. Critical care utilization for the COVID-19 outbreak in Lombardy, Italy: early experience and forecast during an emergency response. JAMA. 2020;323(16):1545-1546. doi:10.1001/jama.2020.4031 (opens in new tab)
  3. Robinson J. Almost a third of hospitals report 'complete outages' of medicines during COVID-19 pandemic. The Pharmaceutical Journal. 13 January 2021. pharmaceutical-journal.com (opens in new tab)
  4. Zdanowicz Z, Laternser C, Crilly CJ, Kan K, Lay AS, Woo JL. Discharge barriers and length of stay following congenital heart surgery: a mixed-methods approach. Journal of the American Heart Association. 2026. 52 of 752 infants (6.9%) had an equipment-delivery or prior-authorization delay. doi:10.1161/jaha.125.047918 (opens in new tab)

Licence and notices

Licence. Code: AGPL-3.0. A commercial licence is available on request. Content: CC BY-NC 4.0.

Independence and data notice. This is personal work, made independently in my own time and on my own equipment. It is not affiliated with, endorsed by, or representative of my employer or any other organisation. It contains no employer data, systems, code or confidential information. All data shown is synthetic.

Not a medical device. Demonstration only. Not for clinical, operational or personal decisions. No warranty. No liability.